
Thyroid Surgery for Nodules, Goitre and Thyroid Cancer in Hyderabad
Consult a surgical oncologist in Hyderabad about a thyroid nodule, goitre or thyroid cancer. Dr. Sanjay Yadagiri reviews your scan and biopsy results, explains whether part or all of the gland needs removing, and plans surgery with care for the voice nerves and parathyroid glands.
Quick answers
- Who performs it?
- Dr. Sanjay Yadagiri, Consultant in Surgical Oncology and Minimal Access Surgery, Hyderabad.
- When is it considered?
- A lump or swelling in the front of the neck; FNAC-positive or suspicious thyroid nodule. Suitability is decided after examination and tests.
- Where are consultations?
- Banjara Hills clinic, Mon-Sat: 1:00 PM - 5:00 PM. Sunday closed.
- How do I book?
- Use the booking form or call +91 70324 76866.
What is Thyroid Surgery?
Thyroid surgery (thyroidectomy) involves removing part or all of the thyroid gland. It is indicated for suspicious nodules, biopsy-proven thyroid cancer, large or compressive goitres, retrosternal extension, and selected cases of hyperthyroidism (Graves' disease, toxic nodule) that have not responded to medical treatment. The two main risks - injury to the recurrent laryngeal nerve (voice) and inadvertent removal of the parathyroid glands (calcium) - are minimised by careful capsular dissection, magnification and, where indicated, intraoperative nerve monitoring. Dr. Yadagiri's surgical oncology background means thyroid cancer cases are planned with full neck assessment and, when needed, central or lateral neck dissection.
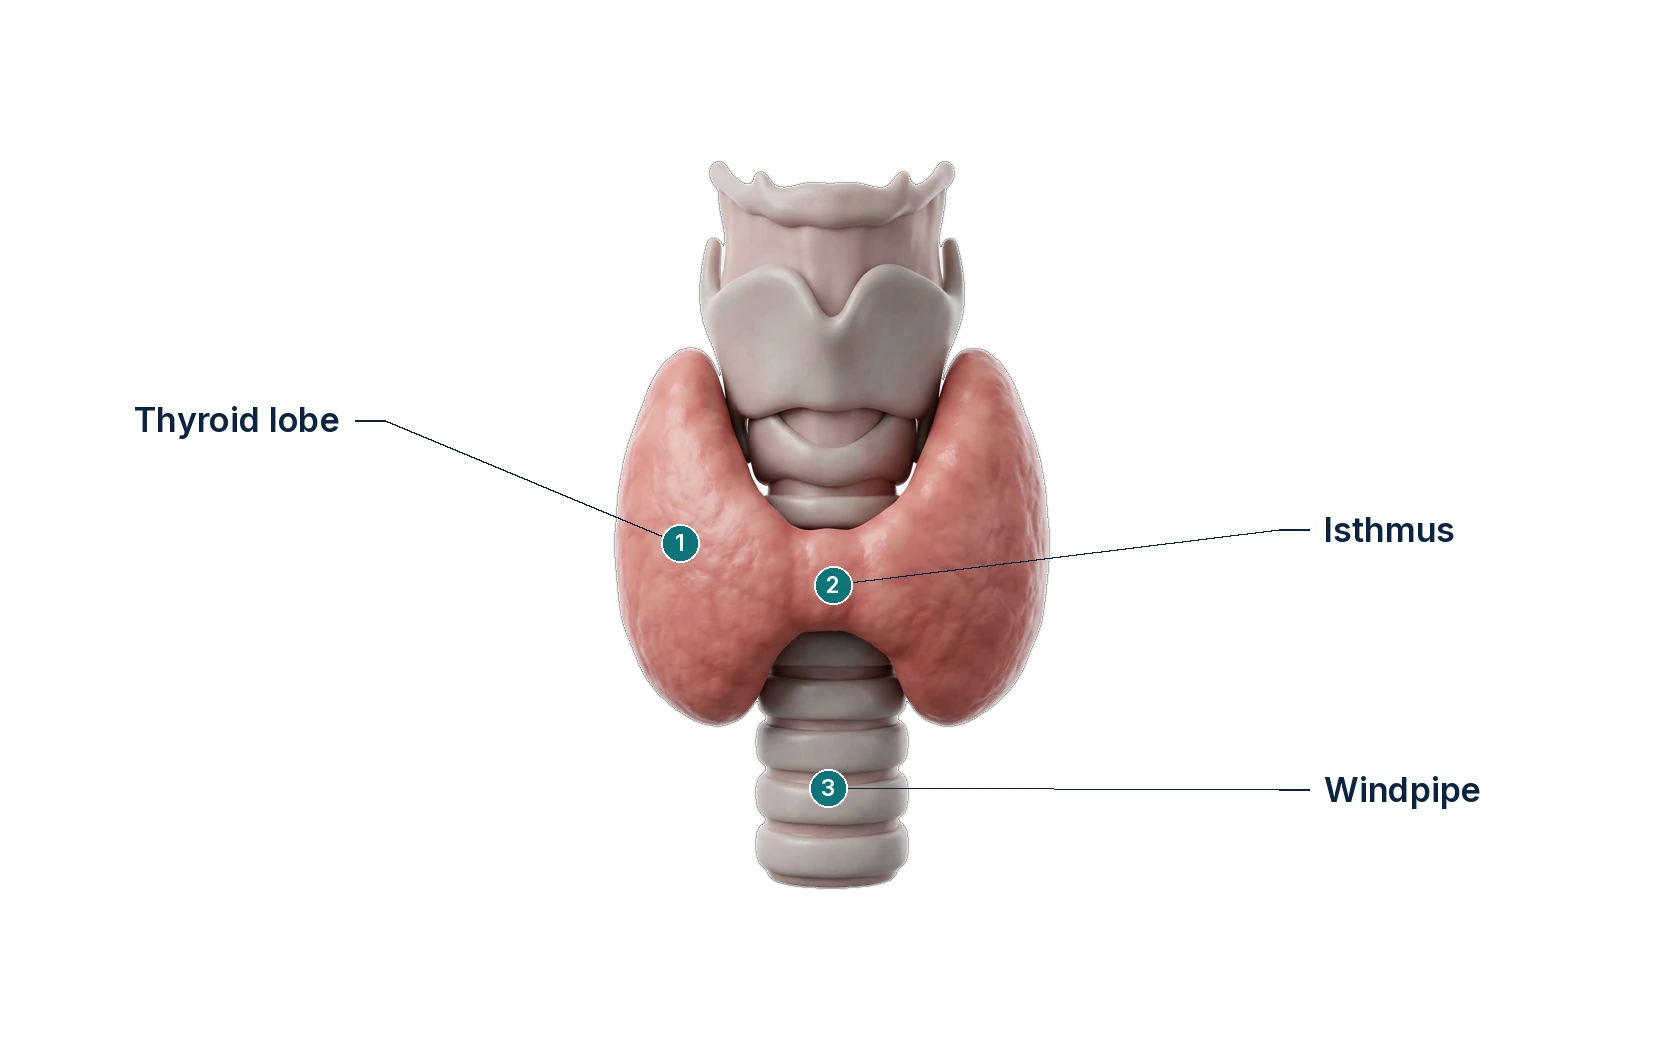
- Thyroid lobe
- Isthmus
- Windpipe
The whole thyroid gland means both lobes and the connecting isthmus, in front of the windpipe. One lobe or the whole gland may be removed; the extent is decided after assessment.
Thyroid findings that may need a surgical opinion
- A lump or swelling in the front of the neck
- FNAC-positive or suspicious thyroid nodule
- Difficulty swallowing or a sense of pressure in the throat
- Change in voice or hoarseness
- Large multinodular goitre, especially with retrosternal extension
- Hyperthyroidism not controlled by medicines or radioiodine
Thyroid surgery options: lobectomy and total thyroidectomy
Lobectomy (hemithyroidectomy)
- • Removes one lobe of the thyroid and usually the isthmus
- • Often used for a single indeterminate nodule or selected small, low-risk cancers
- • Many patients keep enough thyroid function not to need tablets, though some do
- • A completion operation may be advised later if the final pathology needs it
Total thyroidectomy
- • Removes the whole thyroid gland
- • Considered for larger or higher-risk cancers, disease in both lobes, or large goitres
- • Lifelong daily thyroid hormone tablets are needed afterwards
- • Central or lateral neck dissection may be added for thyroid cancer when indicated
The extent of surgery depends on the biopsy result, the size and spread of any cancer, both sides of the gland and your own preferences. Some low-risk thyroid cancers may be managed with lobectomy or, in selected cases, active surveillance. Your options are discussed at consultation.
Recovery Timeline
- Day 0Surgery, sit up and sip the same evening
- Day 1Drain removed, discharge home for most cases
- Week 1Suture or staple removal, voice assessment
- Week 2-4Return to normal activity; thyroid hormone dose finalised
Frequently Asked Questions
Further reading
Independent patient and clinician information used as background for this page:
This page is general information, not medical advice. Your own treatment is discussed after assessment.